

By Eyal Shahar, Brownstone Institute
In a recently published study, researchers from the Czech Republic report a rare, national-level analysis of Covid vaccines and all-cause mortality. Anyone with a critical mind should at least read the exemplary summary by Tomas Fürst on Brownstone and carefully study the figure.

Toward the end of the Brownstone article, Fürst writes:
“Yet, in the Mirror of Erised above, you can see that the vaccine may appear to be 80% effective, even against Covid-unrelated deaths! Still, we are not aware of any vaccine effectiveness studies that tried to correct for this huge HVE [healthy vaccinee effect, E.S.]. This means that all claims of Covid vaccine effectiveness since the beginning of the mass vaccination campaign must be revised. The vaccine’s true efficacy against death from Covid may have been zero, or even negative; we simply don’t know.”
I could not agree more. Repeated model-based claims about millions of saved life-years cannot be reconciled with simple mortality statistics—for example, a contrast of Israel with Sweden in the winter of 2020–2021 or elementary worldwide calculations. Having failed to penetrate the censorship machinery of biomedical journals, I devoted numerous posts to the healthy vaccinee bias and a method to remove it. However, just a few weeks after the Czech study was published, I finally published a peer-reviewed paper on the (corrected) effectiveness of a Covid vaccine. The road to publication was not easy. Even medRxiv refused to post a preprint on the basis of a ridiculous excuse. (“It is not a clinical research article with new data.”)

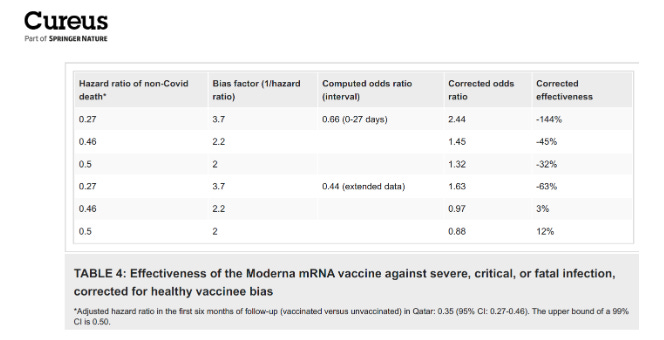
Using published data from Qatar, I was able to remove two key biases, one of which was the healthy vaccinee effect. The other bias, formally called immortal time, arose from excluding early events in the vaccinated, a common practice of vaccine effectiveness studies. Unfortunately, it is too technical to explain here. Removing that bias reduced estimates of effectiveness by a lot—sometimes from over 95 percent to less than 50 percent—and suggested early negative effectiveness.
As I explained in a book (chapter 37), the healthy vaccinee bias cannot be removed by an exact method, so we have two options: to accept the bias or to try to remove it by an imperfect method. In my paper, I justified and applied three correction factors to estimates of vaccine effectiveness. It is called sensitivity analysis. Under every correction, the effectiveness against a severe outcome of two early variants was negative in the first month and near zero, at best, by the time full immunity was reached. The original paper reported 100% effectiveness…
Immortal time and healthy vaccinee are not the only biases in observational studies of Covid vaccines. At least two more should be mentioned:
Vaccinated people were less likely to be tested for Covid than their unvaccinated counterparts, and therefore, they were less likely to be classified as cases of severe Covid and Covid deaths. In the taxonomy of biases, it is called information bias. We have unquestionable evidence that the bias was operating in Israel—“The Pfizer laboratory” —during the first vaccination campaign. This bias has probably affected studies from many countries.
Another source of bias was the timing of the vaccination campaigns, which often coincided with a Covid wave. As a result, the time-at-risk in an unvaccinated status was concentrated at the time of rising infection rates, whereas the time-at-risk in vaccinated status was concentrated at the phase of the decline. It is called confounding by time trends in the risk of the outcome. A few studies tried to prevent this bias by matching on calendar time; many did not.
A perfect storm of biases was operating at that time, and, as Fürst writes, “The true value of the vaccine effectiveness can only be derived from prospective randomized studies.”
I am wondering whether we will ever see them. Will the FDA continue to authorize new mRNA Covid vaccines each year solely based on their ability to generate antibodies? Might we be increasing the risk of an infection with more shots due to class switch to IgG4 antibodies? Should these shots continue to be administered to residents of nursing homes, if negative effectiveness is at least possible, and vaccine-related deaths have undoubtedly happened? Is it ethical to continue to approve a novel gene therapy without a single, well-designed, randomized trial with a mortality endpoint?
The FDA, under a new administration, has recently made progress in the right direction. I hope they will not stop there. Winter is too close for a trial this year, but there is plenty of time for the NIH to write up a Request for Applications for randomized trials next winter. The study population should be residents of nursing homes who can provide consent because that’s the high-risk population. Let’s see a comparison of next-year formulations of mRNA Covid vaccines with placebo, with a mortality endpoint: Covid deaths and all-cause deaths. Perhaps there should be a third arm for the flu shot.

QTR’s Disclaimer: Please read my full legal disclaimer on my About page here. This post represents my opinions only. In addition, please understand I am an idiot and often get things wrong and lose money. I may own or transact in any names mentioned in this piece at any time without warning. Contributor posts and aggregated posts have been hand selected by me, have not been fact checked and are the opinions of their authors. They are either submitted to QTR by their author, reprinted under a Creative Commons license with my best effort to uphold what the license asks, or with the permission of the author.
This is not a recommendation to buy or sell any stocks or securities, just my opinions. I often lose money on positions I trade/invest in. I may add any name mentioned in this article and sell any name mentioned in this piece at any time, without further warning. None of this is a solicitation to buy or sell securities. I may or may not own names I write about and are watching. Sometimes I’m bullish without owning things, sometimes I’m bearish and do own things. Just assume my positions could be exactly the opposite of what you think they are just in case. If I’m long I could quickly be short and vice versa. I won’t update my positions. All positions can change immediately as soon as I publish this, with or without notice and at any point I can be long, short or neutral on any position. You are on your own. Do not make decisions based on my blog. I exist on the fringe. If you see numbers and calculations of any sort, assume they are wrong and double check them. I failed Algebra in 8th grade and topped off my high school math accolades by getting a D- in remedial Calculus my senior year, before becoming an English major in college so I could bullshit my way through things easier.
The publisher does not guarantee the accuracy or completeness of the information provided in this page. These are not the opinions of any of my employers, partners, or associates. I did my best to be honest about my disclosures but can’t guarantee I am right; I write these posts after a couple beers sometimes. I edit after my posts are published because I’m impatient and lazy, so if you see a typo, check back in a half hour. Also, I just straight up get shit wrong a lot. I mention it twice because it’s that important.
There is a a significant number of people who's identity is centered around their noble effort of saving humanity by repeatedly injecting themselves with an experimental genetic modifier. These people will not be dissuaded from taking the injections because of a better analysis of the data or better efficacy trials. In fact, they may get agitated - and possibly violently so - if their access to the injections is prevented due to studies showing the injections are ineffective or even harmful.
We live in a society where there is a sizeable quilt of stitched-together cults, each focused on a delusional belief as it's centerpiece. So hopefully once the COVID injection issue is finally put to rest, the researchers can move on to the causes of the severe mental illness afflicting upwards of half the country.
it is pitiful that the USA, a highly developed country, has settled for such crap science as the pharma companies have provided. It is great to hear Pres Trump is calling them out, insisting on real studies, not those concocted to show effectiveness and safety. e.g., the original studies dropped subjects who showed ill-effects in the first 2 weeks after injection. why? because they said the vax would take effect for 2 weeks. so, e.g., i get a vax and drop dead in 2 minutes--that subject is tossed. I am not vaxed and never will be.